

Share
Start here
Thyroid cancer at a glance
The thyroid is a small gland at the front of the neck that produces hormones regulating many body functions. Thyroid cancer includes several distinct diseases. Papillary and follicular cancers are often slow growing and highly treatable. Medullary cancer needs a different testing and treatment pathway. Anaplastic cancer is uncommon, fast growing and requires urgent specialist care. Knowing your exact type helps you understand which tests and treatments may apply to you.
This guide covers the main adult thyroid cancers, including oncocytic cancer, previously called Hürthle cell cancer. Not everyone needs the whole thyroid removed, radioactive iodine treatment or lifelong medicine doses to keep thyroid-stimulating hormone (TSH) low. These options are explained below. Your treatment should match the risk posed by your cancer. Some very small, low-risk papillary cancers can be monitored carefully rather than operated on immediately.
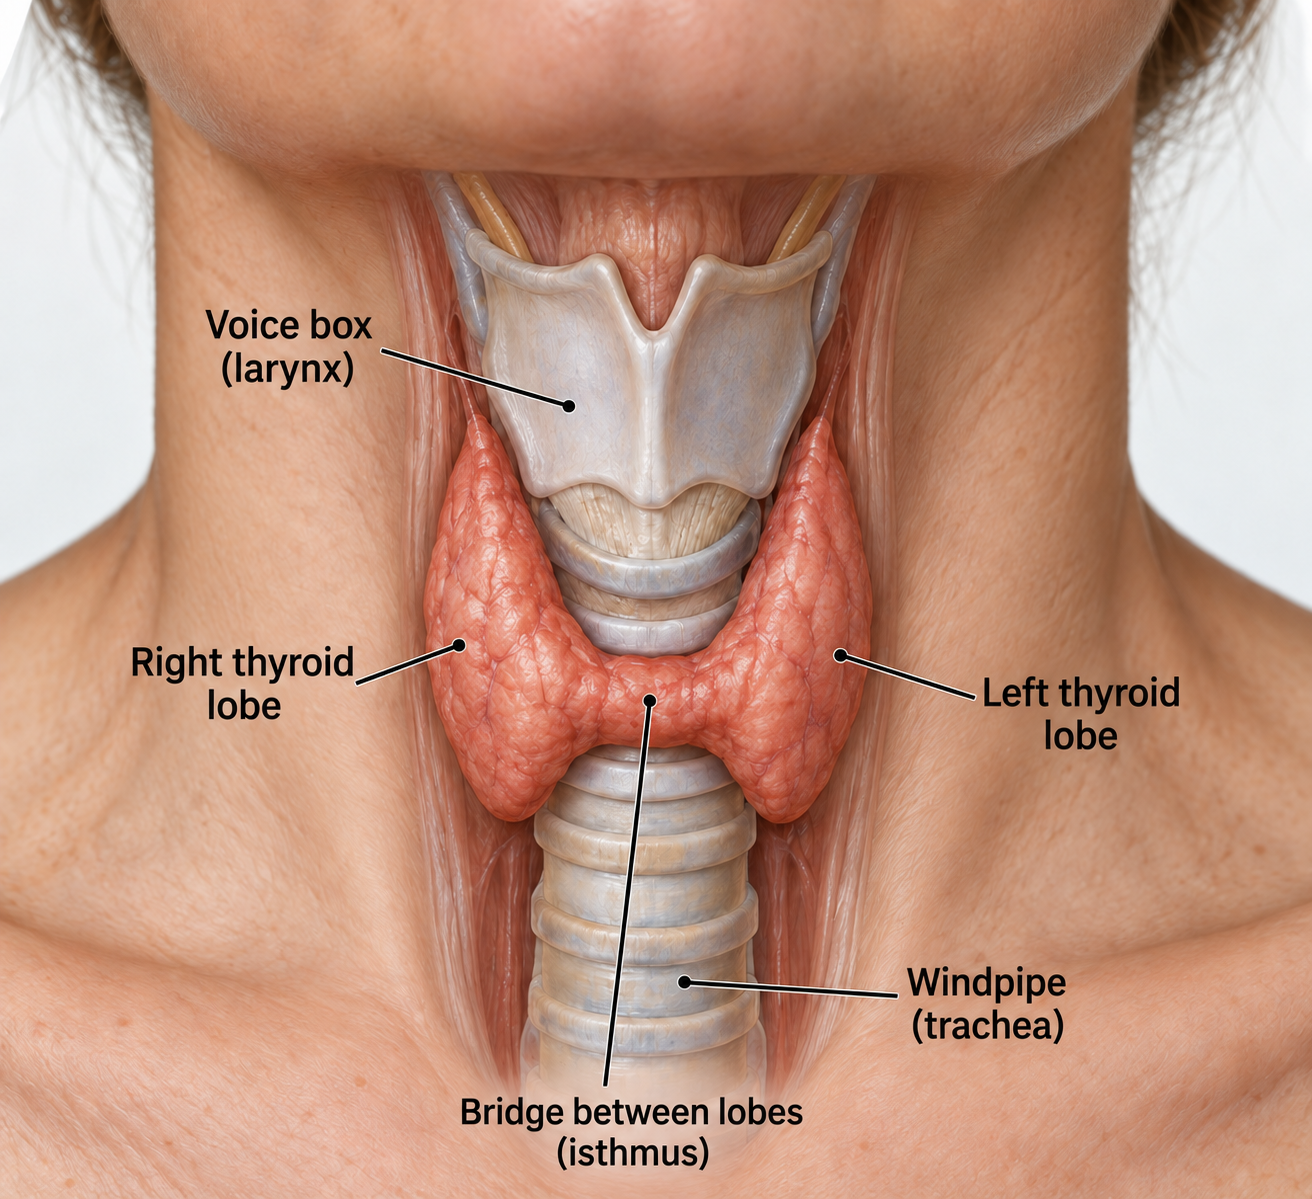
Symptoms and warning signs
A new or enlarging neck lump, persistent hoarseness, difficulty swallowing or enlarged lymph nodes in the neck should be assessed. Lymph nodes are small structures that are part of the immune system. Most thyroid nodules (lumps) are benign, meaning they are not cancer, and thyroid hormone blood tests may be normal even when a cancer is present. A normal thyroid blood test cannot rule out cancer in a suspicious lump.
A rapidly enlarging neck swelling, noisy breathing, breathlessness or inability to swallow needs urgent assessment. These symptoms can indicate pressure on the airway and should not wait for routine testing. After thyroid surgery, sudden neck swelling or breathing difficulty is an emergency because bleeding can compress the airway.
Making this information useful to you
A cancer diagnosis can arrive before you have had time to understand the tests. You do not need to learn every treatment name at once. Begin with the exact diagnosis, where the cancer is, and what the team recommends next. A relative or friend can join the appointment if you would find that helpful. Ask for an interpreter when language makes a discussion harder; important decisions should not depend on guessing unfamiliar words.
This guide explains possibilities, not a prescription for your situation. Your pathology, scan findings, general health, previous treatment and priorities determine which possibilities apply. Two people with the same cancer name may appropriately receive different treatment. If a recommendation differs from something you have read, ask the team to explain the reason and the evidence behind it.
Keep a list of medicines, allergies and other health conditions, including non-prescription products, vitamins and herbal remedies. Tell the team about previous cancer treatment, pregnancy or breastfeeding, and anything that could affect attending appointments. Do not stop an established medicine without advice. Bring your questions in the order that matters most to you, so that the most important concern is discussed first.
Understand
The main thyroid cancer types
Papillary, follicular and oncocytic cancers are often grouped as differentiated thyroid cancers. This means their cells retain some features of normal thyroid cells. Medullary and anaplastic cancers need different approaches to care.
- Papillary cancer: the most common differentiated thyroid cancer. It may spread to neck lymph nodes but often remains highly treatable.
- Follicular cancer: diagnosed partly by finding cancer cells growing through the tumour’s outer covering (capsule) or into blood vessels. It can spread through the bloodstream, including to lung or bone.
- Oncocytic cancer: a differentiated cancer with distinct features; it may be less likely to take up radioactive iodine.
- Medullary cancer: arises from C cells, which make a hormone called calcitonin, rather than the cells that make the main thyroid hormones. Changes in a gene called RET can sometimes be inherited and may affect care for you and your family.
- Anaplastic cancer: a fast-growing cancer needing rapid diagnosis, tests for gene changes (molecular testing) and coordinated treatment.
Poorly differentiated cancers have cells that look less like normal thyroid cells. In some ways they behave between well-differentiated and anaplastic cancers, so they need specialist treatment planning. Thyroid lymphoma and cancers spreading to the thyroid from another organ have separate pathways. Your team needs a sufficiently clear diagnosis from the tissue or cell sample before choosing treatment for a neck lump.
Factors that increase risk
Previous radiation exposure to the neck, especially in childhood, and some inherited syndromes increase risk. Family history is relevant, but many patients have no identifiable inherited cause. Most nodules are not cancer, and routine repeated imaging of every harmless nodule can create unnecessary worry. The ultrasound features, size, symptoms and personal history guide whether biopsy is useful.
Everyone with medullary thyroid cancer should discuss testing for an inherited RET gene change (germline testing), with genetic counselling, even without a family history. Counselling helps you understand what the result could mean for you and your relatives. An inherited change may indicate multiple endocrine neoplasia type 2 (MEN2), a condition that can affect several hormone-producing glands.
In that setting, testing for a pheochromocytoma (an adrenal tumour that can release dangerous amounts of stress hormones) and other associated conditions is important before thyroid surgery. Tumour RET testing for treatment selection is not the same as inherited testing.
Thyroid hormones and TSH
The pituitary gland, at the base of the brain, produces thyroid-stimulating hormone (TSH), which signals the thyroid to make hormone. After total thyroid removal, levothyroxine replaces the missing hormone. In selected differentiated cancers, a dose that keeps TSH lower than usual may reduce stimulation of any remaining cancer cells. The target depends on the chance of cancer returning, the response to treatment and risks such as heart rhythm problems or bone loss.
Keeping TSH below the usual range (TSH suppression) is not a lifelong requirement for everyone and is not the anticancer strategy for medullary or anaplastic disease. The dose may change as the response becomes clearer. Do not adjust levothyroxine based only on symptoms or a single result without discussing the intended target.
Tests and diagnosis
How cancer is diagnosed
Ultrasound assesses the thyroid and neck lymph nodes. When needed, fine-needle aspiration uses a thin needle to collect cells from a thyroid lump or a suspicious lymph node. Some samples clearly show whether cancer is present. Others are indeterminate, meaning the result is uncertain. For example, cells alone cannot show whether a follicular-pattern tumour has grown through its outer covering or into blood vessels.
Removing one half of the thyroid (a lobe), or molecular testing in selected circumstances, may help clarify the diagnosis.
An indeterminate result means the sample has not given a clear answer; it does not confirm cancer. Ask about the estimated chance of cancer, whether another sample would help and how each option would affect your care. For some nodules, a molecular test can help decide whether surgery is needed. It is not needed for every nodule, and its benefits, limitations and cost should be discussed.
This use of molecular testing is different from testing a confirmed cancer to choose treatment, described below. A core biopsy, which takes a small piece of tissue rather than just cells, may be needed for some rapidly growing tumours or suspected lymphoma.
Understanding your pathology report
Your pathology report describes what was found in the cell or tissue sample. It includes the cancer type and, after surgery, its size, growth into nearby tissue, whether cancer reaches the edges of the removed tissue (margins), and whether removed lymph nodes contain cancer.
After surgery it helps estimate both the stage and the chance of recurrence. These are related but different: the stage describes how far cancer has grown or spread and helps estimate the outlook; the chance of it returning helps guide follow-up and additional treatment. In differentiated cancer, age influences stage classification, so stage numbers should not be compared casually with those of other cancers.
For medullary cancer, blood tests measure calcitonin and carcinoembryonic antigen (CEA). These are markers that can help track the cancer. Their levels and change over time can help with monitoring but do not replace imaging and clinical assessment.
Differentiated cancer follow-up often measures thyroglobulin, a protein made by thyroid cells. The team also checks for thyroglobulin antibodies, which can affect the test result, and considers how much normal thyroid tissue remains. These markers are not interchangeable between cancer types.
Scans and staging tests
Neck ultrasound is central. Computed tomography (CT) or magnetic resonance imaging (MRI) may be needed when disease is bulky, extends beyond the thyroid or involves deeper structures. Chest imaging and other scans depend on the cancer type, markers and symptoms. Radioiodine scans are relevant only when the cancer can use iodine; positron emission tomography combined with CT (PET-CT) is reserved for appropriate situations rather than every new thyroid cancer.
Tell the nuclear medicine team about recent scans using iodine-containing contrast dye, iodine supplements and relevant medicines because they can affect radioiodine planning. Essential diagnostic imaging should not be withheld simply from fear of delaying iodine treatment; the teams can coordinate timing. Voice assessment, sometimes including examination of the vocal cords, is important before surgery when indicated.
Molecular testing in advanced disease
Molecular testing looks for gene changes in cancer cells that may help your team choose a targeted medicine. The timing and type of test depend on which thyroid cancer you have.
- Differentiated thyroid cancer: if the cancer is growing despite radioactive iodine, or no longer responds to it, tumour molecular testing is strongly recommended before starting medicines that treat cancer throughout the body. A panel that checks several genes can identify treatment targets such as RET or NTRK gene fusions (parts of different genes joined together) and BRAF V600E (a specific gene change). Testing is not routinely needed solely because cancer has spread if it is stable and no medicine that treats cancer throughout the body, or treatment to help the cancer take up iodine again, is planned.
- Medullary thyroid cancer: everyone should be offered testing for an inherited RET gene change, with genetic counselling. In advanced disease, the tumour should also be tested for RET changes if inherited testing is negative, uncertain or still pending, especially when targeted treatment is being considered. A known disease-causing inherited RET result can already guide treatment.
- Anaplastic thyroid cancer: rapid BRAF V600E testing and broader tumour molecular profiling are recommended at diagnosis because the results can guide urgent treatment.
A gene change found in the tumour does not automatically mean it is inherited or that relatives are at risk. Your team can explain whether a separate inherited-gene test is needed.
Preparing for your appointment
For your consultation or a second opinion, bring a CD containing your scan images (DICOM format) and the software needed to view them, along with the written scan reports. Bring your biopsy report and ask whether the pathology slides or tissue blocks are needed for specialist review or additional tests. Keep originals safe and agree how borrowed material will be returned. Having the actual images allows the team to compare changes and plan treatment accurately.
A repeat test is sometimes needed because an earlier sample was too small, a scan did not cover the necessary area, or a new result will change treatment. Ask what question the test will answer, how it may affect the plan, and when you should expect the result. A result described as uncertain does not automatically mean the cancer is worse. Sometimes discussion between the radiologist, pathologist and treating specialists resolves the uncertainty without another procedure.
Before a scan or procedure, mention kidney problems, previous contrast reactions, implanted devices, diabetes medicines, blood-thinning medicines and the possibility of pregnancy. Follow the testing centre's instructions about food, drink and medicines. If you have not received those instructions, contact the centre rather than making changes yourself.
Planning your treatment
Understanding your stage
Subtype- and age-specific thyroid staging
First check the thyroid cancer subtype and your age at diagnosis. The same stage number can mean very different things in different thyroid cancers. The chance of cancer returning (recurrence risk) is assessed separately from stage.
Lymph nodes are small immune-system structures. Regional nodes are those near or draining the cancer’s starting area; distant spread means cancer has reached a site outside that regional area. Stages describe findings, not a sequence that everyone will pass through.
Differentiated cancer: younger than 55
For papillary and follicular cancers, including oncocytic cancers, only two stage groups apply at this age.
Stage 1 (I)
Cancer has not spread to distant parts of the body. The tumour may be any size and may involve nearby tissue or regional nodes.
Stage 2 (II)
Cancer has spread to distant parts of the body, for example the lungs or bones. There are no stages 3 or 4 in this age group.
Differentiated cancer: age 55 or older
Age is counted at diagnosis. These groups use tumour extent as well as nodes and distant spread.
Stage 1 (I)
Tumour no larger than 4 cm, confined to the thyroid, without regional node or distant spread.
Stage 2 (II)
A larger tumour, regional nodes or visible growth into the nearby muscles at the front of the neck (strap muscles), without more extensive invasion or distant spread.
Stage 3 (III)
Invasion into specified nearby structures such as the voice box, windpipe, food pipe or voice nerve, without distant spread.
Stage 4 (IV)
IVA means very extensive local invasion, such as tissue in front of the spine or growth around major blood vessels. IVB means distant spread.
Medullary thyroid cancer: all ages
The age-55 division does not apply to medullary thyroid cancer.
Stage 1 (I)
Tumour no larger than 2 cm, confined to the thyroid, without nodes or distant spread.
Stage 2 (II)
A larger tumour or limited nearby muscle invasion, without involved nodes or distant spread.
Stage 3 (III)
Lymph nodes in the central part of the neck are involved, without the more extensive features of stage 4.
Stage 4 (IV)
IVA includes lymph nodes at the side of the neck or specified local invasion; IVB means very extensive local invasion; IVC means spread to distant parts of the body.
Anaplastic thyroid cancer: all ages
All anaplastic thyroid cancer is assigned stage 4 because of its aggressive biology. This does not mean that every person with anaplastic cancer has cancer in distant parts of the body.
Stage 4A (IVA)
Cancer remains within the thyroid, without regional nodes or distant spread.
Stage 4B (IVB)
Cancer involves regional nodes or grows outside the thyroid, but there is no distant spread.
Stage 4C (IVC)
Cancer has spread to distant parts of the body.
The stage must be interpreted for your particular type of thyroid cancer. Cancer in a neck lymph node does not automatically mean stage 4. Your team can explain which system applies and how the findings affect treatment.
Clinical stage comes from examination, biopsies and scans. Pathological stage can add information from surgery; a prefix such as yp means the tissue was assessed after treatment. A revised assessment does not necessarily mean the cancer grew while you were waiting. Grade describes the cells’ behaviour and is different from stage.
How your treatment plan is chosen
The plan depends on the type, extent, rate of growth, symptoms and your health and preferences. Your team may include a thyroid surgeon, a hormone specialist (endocrinologist), a doctor who examines tissue samples (pathologist), a specialist in radioactive scans and treatments (nuclear medicine), and cancer specialists. Ask whether the main goal is to cure the cancer, reduce the chance of it returning, control its growth or relieve a particular problem.
For low-risk differentiated cancer, avoiding unnecessary treatment can be as important as treating cancer that poses a genuine risk. Faster-growing cancers need prompt care. A monitoring plan that is suitable for one person may not be safe for another. Your team should explain which features of your cancer guide this decision.
Active surveillance for selected papillary cancers
Some small, low-risk papillary cancers can be monitored with expert ultrasound and clinical review. Suitability depends on location, whether it is growing into nearby structures or has spread to lymph nodes, whether regular follow-up is possible, and your preferences. A tumour close to a critical structure or showing progression may not be suitable. Active surveillance means regular checks with an agreed plan for when treatment would be needed.
Ask how often scans are needed, what amount or pattern of growth would prompt surgery, and whether you are comfortable with monitoring. Surgery remains an option if circumstances or preferences change. Evidence for surveillance in selected papillary disease should not be extended to medullary or anaplastic cancer.
Questions specific to thyroid cancer
Ask whether removing one half of the thyroid (lobectomy) is enough, why removal of the whole thyroid (total thyroidectomy) is being recommended, and whether radioactive iodine is likely to help. Discuss the surgeon's experience, voice and calcium risks, and the plan for thyroid hormone afterwards. If medullary cancer is diagnosed, ask about inherited testing and screening for associated endocrine conditions before surgery.
Questions to ask your care team
- What is the exact cancer type and stage, and are any important results still pending?
- Is the aim to cure the cancer, reduce the chance of recurrence, control it, or relieve a particular symptom?
- What benefit do you expect from this option, and what are the reasonable alternatives for me?
- How will treatment affect everyday activities, fertility, sexual health and the things I most value?
- How will we know whether it is working, and when will we review the plan?
- Who should I contact between visits, including at night or over a weekend?
Clinical trials and newer treatments
A clinical trial can be worth considering at diagnosis or when treatment needs to change. Trials ask a defined question; some compare established treatments and others study a newer approach. Eligibility depends on the cancer, previous treatment, test results and health. Taking part is voluntary, and choosing not to participate does not remove your right to standard care. Ask about extra visits, possible randomisation, costs, travel, side effects and what happens when the study ends.
Newer treatments are considered using the clinical evidence, recognised guidelines and the exact cancer type, biomarkers and previous treatment. Some options have less mature evidence than established treatments. Ask what is known, what remains uncertain and whether a clinical trial would be appropriate.
Your priorities and supportive care
Tell the team what you are hoping treatment will make possible: returning to work, caring for family, keeping independence, reducing pain or attending an important event. These priorities can influence a choice between reasonable options. If the likely benefit is small and the burden is substantial, discussing a less intensive approach is appropriate. Decisions can be revisited when your health or circumstances change.
Supportive and palliative care help with symptoms, sleep, mood, family concerns and planning. They can be provided alongside treatment intended to cure or control cancer. A referral does not mean that active treatment is ending. If the cancer cannot be cured, ask what treatments may help you live longer or more comfortably and how their burdens compare with their likely benefits.
Treatment options
Surgery for differentiated cancer
The first options below apply to differentiated thyroid cancers, including papillary, follicular and oncocytic cancer. Medullary and anaplastic cancers have their own treatment sections further down. You do not need every treatment listed here.
Lobectomy removes one half of the thyroid and may be sufficient for selected localised cancers. Total thyroidectomy removes the whole gland and is used when risk or extent warrants it. The choice depends on tumour size and features, spread, other nodules and whether radioactive iodine is expected to be useful. After a lobectomy, the final tissue results may show that removing the remaining half of the thyroid would be helpful. This second operation is called a completion thyroidectomy.
If lymph nodes are suspected or confirmed to contain cancer, the surgeon may need to remove the group of nodes in that part of the neck. More extensive node surgery is not automatically better when there is no evidence it will help. Ask how the operation balances cancer control with risks to the nerves that control the vocal cords (recurrent laryngeal nerves) and the small glands near the thyroid that regulate calcium (parathyroid glands). A well-planned first operation is particularly valuable.
Radioactive iodine
Radioactive iodine, or RAI, can destroy iodine-absorbing thyroid tissue and some differentiated thyroid cancer cells after appropriate surgery. It is not required for every papillary or follicular cancer and is not a treatment for medullary or anaplastic cancer. The decision depends on recurrence risk, remaining disease and the likelihood that the cancer will take up iodine.
Preparation may involve injections of manufactured TSH (recombinant TSH) or temporarily stopping thyroid hormone tablets, together with a short low-iodine diet according to local instructions. Do not undertake hormone withdrawal or a restrictive diet without a plan. Treatment is given through nuclear medicine, which provides individual radiation-safety instructions about contact with others, sleeping arrangements and return to work.
RAI must not be given during pregnancy, and breastfeeding requires advance planning and clear instructions from your team about when to stop. Ask about the recommended interval before attempting pregnancy after treatment. Salivary gland symptoms, dry mouth, altered taste and other side effects can occur. Repeated doses should have a clear expected benefit rather than being given simply because a marker remains detectable.
Thyroid hormone replacement and monitoring
After total thyroidectomy, daily levothyroxine is essential. Some people also need it after lobectomy. Take it consistently as advised, and discuss timing with food, calcium, iron and other medicines that can alter absorption. Blood tests guide dose changes; the target is specific to your cancer and health, not always the usual laboratory range.
Symptoms such as palpitations, tremor, fatigue or feeling unusually cold deserve review, but can have several causes. Avoid switching doses or stopping treatment without advice. Pregnancy, weight changes, other medicines and recovery from treatment can alter requirements. Keep the care team informed when these circumstances change.
If differentiated cancer returns or spreads
Small stable findings may be monitored when treatment risks outweigh immediate benefit. Cancer that returns in or near the original area can sometimes be treated with further surgery or selected local procedures. RAI can help cancer that still takes up iodine, but cancer that no longer takes up iodine or progresses despite appropriate RAI needs a different strategy. A rise in a blood marker alone does not always mean you need to start a cancer medicine immediately; your team also weighs its likely benefit and side effects.
If cancer no longer responds to radioactive iodine (RAI-refractory cancer) and is growing, causing symptoms or threatening important structures, targeted medicines may help.
Lenvatinib or sorafenib may be used. Each blocks several growth-related signals and is called a multikinase inhibitor. Cabozantinib may be an option for eligible patients after treatment targeting vascular endothelial growth factor (VEGF), a signal involved in blood-vessel growth. Cancers with a RET or NTRK gene fusion may respond to medicines that target that particular change (selective inhibitors). The order of treatment depends on the cancer’s features, previous treatment, speed of growth and access to medicines.
Radiotherapy, surgery or a procedure that destroys tumour tissue (ablation) can help treat a troublesome area of cancer in bone, the brain or another site. Discuss a suitable clinical trial when established options are limited.
Medullary thyroid cancer
Surgery is central for localised medullary cancer, usually with removal of the thyroid and appropriate lymph node treatment. Before surgery, an associated pheochromocytoma must be considered and managed if present, particularly with inherited RET disease. This prevents potentially dangerous hormone-related complications during an operation.
RAI does not treat medullary cancer. Follow-up uses calcitonin, CEA, imaging and symptoms. Slowly changing markers without threatening visible disease may be monitored. Progressive or symptomatic advanced disease may be treated with a selective RET inhibitor such as selpercatinib when a suitable RET mutation is present, or other targeted medicines such as vandetanib or cabozantinib when appropriate. Cabozantinib comes in different forms for different uses; they should not be substituted for one another.
Genetic counselling can help relatives decide about testing and preventive care if an inherited change is found. The timing of preventive thyroid surgery in a relative depends on the exact mutation and specialist assessment, not simply on another family member's age at diagnosis.
Anaplastic thyroid cancer
For anaplastic cancer, your team will promptly coordinate checks on your breathing, a biopsy, scans to assess the cancer’s extent, and molecular testing. The team should assess whether surgery can remove all the cancer and whether radiotherapy and medicines that work throughout the body can help. Avoiding a prolonged sequence of uncoordinated investigations is important. Symptoms affecting breathing or swallowing may require immediate supportive measures.
BRAF V600E-positive disease may be treated with dabrafenib plus trametinib in the appropriate setting. Other uncommon gene changes that can be targeted by a medicine may offer additional options, and trials are important. Surgery, radiotherapy and chemotherapy are selected according to extent and response. Treatment may sometimes shrink disease enough to reconsider surgery or radiotherapy, but this is not guaranteed.
Because the disease can progress quickly, discuss both anticancer treatment and symptom support early. Honest conversations about likely benefit, airway decisions and personal priorities can reduce uncertainty. Supportive care should be available from the start and does not depend on stopping active treatment.
Understanding newer treatment options
Selective inhibitors have changed care for some advanced thyroid cancers, but the mutation, cancer type, age and prior-treatment requirements differ by medicine and treatment setting. A RET fusion in differentiated cancer is not identical to a RET mutation in medullary cancer. Evidence for one does not automatically establish benefit in the other.
The treatment team should use current evidence and specialist guidelines. Treatment options can expand while older patient resources retain earlier restrictions. Conversely, not every promising study establishes a routine treatment. Ask whether a proposed treatment is established, guideline-supported in your setting, or part of a trial.
Managing side effects
Voice, calcium and recovery after surgery
Temporary hoarseness can occur after surgery, but persistent voice change, choking or swallowing problems need assessment. Speech and swallowing support can help when needed. Low calcium may cause tingling around the mouth or in the fingers, cramps or spasms; report these promptly and follow the calcium and vitamin D plan. Severe symptoms need urgent care.
The parathyroid glands regulate calcium and may recover gradually after surgery, although some patients need longer-term replacement. Blood tests help adjust treatment. Do not assume that a higher calcium dose is always safer. Sudden neck swelling, tightness or breathing difficulty after surgery is an emergency, even after discharge.
Targeted treatment effects
Multikinase inhibitors can cause high blood pressure, diarrhoea, fatigue, soreness, redness or peeling of the hands and feet, weight loss and protein in the urine. Some treatments affect liver tests, heart rhythm or bleeding risk. Regular monitoring and early dose adjustments help safe use. Report severe headache, chest pain, black stools, significant bleeding or a new wound problem urgently.
Medicines that target a specific gene change also need safety checks and a review of how they interact with other medicines. Targeted treatment can still cause side effects. Tell the team about planned dental work or operations because some drugs affect healing. Keep a record of blood pressure if advised, and do not take additional supplements or over-the-counter remedies without checking interactions.
Keeping treatment manageable
Keep the team's contact details available and know where to go outside clinic hours. Report side effects early rather than waiting until the next appointment. A short record of symptoms, temperature, fluid intake and medicines can help the team decide what is needed. Do not change cancer medicine doses, restart a stopped treatment, or use leftover antibiotics without instructions. A planned delay or dose adjustment can be an important part of safe treatment.
If you receive treatment that can lower white blood cells, a temperature of 38°C (100.4°F) or higher needs urgent advice. Follow any lower threshold or additional instructions your team gives you. Chills, sudden weakness, confusion or feeling very unwell also need urgent assessment, even without a fever. Do not wait for a blood test appointment or try to hide the fever with medicine before speaking to the team.
Severe breathlessness, chest pain, a new seizure, sudden weakness, heavy bleeding or collapse require emergency care. New severe back pain with leg weakness, numbness around the bottom, or loss of bladder or bowel control also needs immediate assessment. Contact the nearest emergency service when necessary; a website contact form or routine messaging service is not an emergency pathway.
Eating, drinking and energy
Treatment may change appetite, taste, bowel habits and energy. Small, frequent meals and foods containing protein can be easier than large meals. Ask for dietitian support if weight is falling, swallowing is difficult, or you are avoiding many foods. There is no single diet that treats cancer, and severe restriction or prolonged fasting can make it harder to tolerate treatment. Check supplements with your team because some interact with medicines.
Take anti-sickness medicine as prescribed and report vomiting that prevents you keeping down fluids or essential medicines. Seek advice for persistent diarrhoea, dizziness, very little urine or increasing weakness. Fluid recommendations may need adjustment if you have heart or kidney disease. Mouth ulcers, pain or infection that interferes with eating should be treated promptly rather than accepted as unavoidable.
Gentle movement, short walks and planned rest may help fatigue, but activity should match your condition and any surgical or bone-safety restrictions. Fatigue can also reflect anaemia, infection, hormone changes, pain, poor sleep or low mood. Let the team assess a marked or persistent change. Accepting help with shopping, transport or meals can conserve energy for the activities that matter to you.
Live well
Follow-up after treatment
Differentiated cancer follow-up combines examination, neck ultrasound when indicated, TSH and appropriate thyroglobulin testing. Antibodies and remaining thyroid tissue can affect interpretation, especially after lobectomy. The plan changes according to response: someone with an excellent response may need less intensive monitoring than someone with persistent disease.
Medullary cancer is followed with different blood markers, and anaplastic cancer needs closer assessment during care. Do not compare isolated marker numbers between different patients or laboratories without context. Ask which result would trigger additional imaging and which can be watched. A new neck lump, voice change, persistent bone pain or breathing problem should be reported between appointments.
Long-term care includes hormone balance, heart and bone health, and support for anxiety about recurrence. Many people return to usual activities, but fatigue or symptoms deserve attention even when cancer tests are reassuring. Thyroid cancer should not be dismissed as an easy cancer when treatment or uncertainty is affecting your life.
Emotional and practical support
Feeling frightened, angry, sad or uncertain is understandable. You do not have to appear positive all the time. Ask about counselling, psycho-oncology, support groups or a social worker if worry is affecting sleep, relationships or daily life. Persistent depression, panic or thoughts of self-harm need prompt professional help. Caregivers may need their own support and breaks; one person should not have to manage every appointment and household task alone.
It can help to agree who will update relatives and how much information you want shared. Children usually benefit from honest, age-appropriate explanations and reassurance about who will care for them. Ask permission before discussing private medical information with others. If concentration or memory is difficult, use reminders, a calendar and a trusted companion at important consultations.
Relationships, fertility and sexual health
Cancer and treatment can affect desire, comfort, fertility, body image and confidence. These are valid medical concerns. Raise fertility questions before treatment when possible, because some protective options need to be arranged early. The right approach depends on age, the treatment and how urgently it must start. Do not assume that absent periods or reduced fertility means pregnancy is impossible. Ask about contraception and the safe timing of pregnancy for your specific medicines.
Explain any pain, dryness, erection difficulties or changes in intimacy to the team. Appropriate treatments, rehabilitation and counselling can help. You can choose how much to involve a partner. Advice about hormone-containing treatments needs to take the cancer type and treatment into account; do not start them without discussing suitability.
Planning ahead while living well
Ask for a clear follow-up plan and know which symptoms should be reported between visits. Continue care for other conditions and discuss vaccinations with your oncology team; the timing and suitability of live vaccines can change during treatment. Avoid tobacco and ask for practical cessation support if needed. Activity, food and sleep plans should be realistic for your health rather than another source of pressure.
If treatment is long term, arrange periodic discussions about what is helping, what is difficult and what you want next. Planning for future care can protect your preferences and reduce uncertainty for family. You can discuss who should help with decisions if you become too unwell to speak for yourself, while continuing treatment and everyday life now.
Sources and further reading
For more information, explore these resources from the National Cancer Institute (NCI) and other medical organisations. The linked organisations have not reviewed or endorsed this CTI guide. Your care team can explain how the information applies to you.
- NCI: Thyroid Cancer Treatment (PDQ®)–Patient Version
- ASCO guideline collection and update status
- ESMO thyroid cancer guideline
- ESMO systemic therapy update, 2022
- EMA: selpercatinib product information
Staging and risk-group references
AJCC 8th edition; separate rules for differentiated, medullary and anaplastic thyroid cancers.
Medicine approval and prescribing references
These official records describe licensed uses and prescribing information for the medicines named in this guide. Approval depends on the cancer type, biomarkers, previous treatment, combination and formulation. Some uses discussed in the guide are off-label: outside the medicine’s licence, with evidence from clinical guidelines or studies. FDA or EMA approval does not establish approval or availability in India.
- Cabozantinib capsules (Cometriq) — FDA prescribing information · Approval history. Progressive metastatic medullary thyroid cancer. Capsules and tablets are different products.
- Cabozantinib tablets (Cabometyx) — FDA prescribing information · Approval history. Differentiated thyroid cancer after previous VEGFR-targeted treatment, when radioactive iodine is ineffective or unsuitable.
- Dabrafenib — FDA prescribing information · Approval history. With trametinib for eligible BRAF V600E-positive anaplastic thyroid cancer.
- Lenvatinib — FDA prescribing information · Approval history. Progressive differentiated thyroid cancer that does not respond to radioactive iodine.
- Levothyroxine — FDA prescribing information · Approval history. Thyroid hormone replacement and selected TSH suppression.
- Radioactive iodine (sodium iodide I-131) — FDA prescribing information · Approval history. Selected thyroid cancers; this does not cover every thyroid cancer subtype.
- Selpercatinib — FDA prescribing information · Approval history. RET-mutated medullary cancer or RET fusion-positive thyroid cancer, within the label’s treatment criteria.
- Sorafenib — FDA prescribing information · Approval history. Progressive differentiated thyroid cancer that does not respond to radioactive iodine.
- Thyrotropin alfa (Thyrogen; recombinant TSH) — FDA prescribing information · Approval history. Follow-up testing and selected remnant ablation after thyroid surgery; the ablation licence excludes known distant metastases.
- Trametinib — FDA prescribing information · Approval history. The thyroid indication is with dabrafenib for eligible BRAF V600E-positive anaplastic cancer.
- Vandetanib — FDA prescribing information · Approval history. Symptomatic or progressive medullary thyroid cancer that cannot be removed or has spread.
Additional medicine approval notices
These records explain the specific medicine uses and eligibility requirements discussed in this guide.
Clinical guidelines and recommendations
Related care
Meet our doctors



Where to get care




